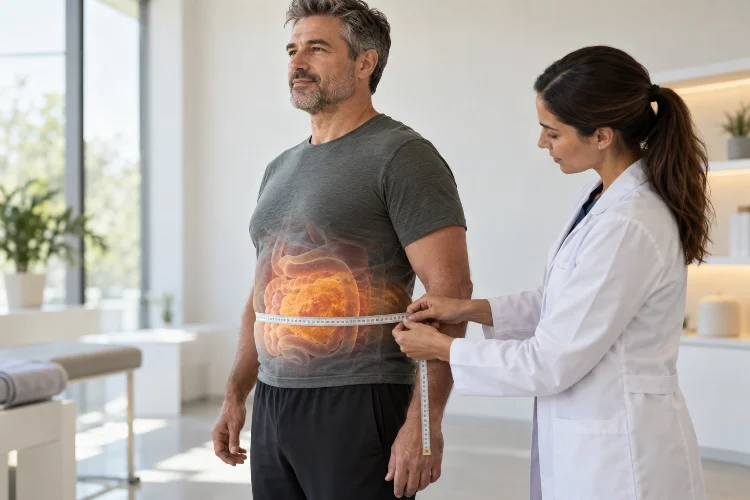
Two people can weigh exactly the same and have very different metabolic health. One may carry more fat just beneath the skin, while another stores a larger proportion deep inside the abdomen around internal organs.
That deeper fat is known as visceral fat, and its location matters.
Body weight and BMI are useful screening tools, but they do not tell us where fat is stored, how much muscle a person has, or whether excess fat is accumulating around organs.
Also Read
The American Heart Association notes that abdominal obesity, often estimated through waist circumference, can provide cardiovascular risk information beyond BMI alone.
Visceral adipose tissue is especially important because it is metabolically active. It releases fatty acids, hormones, and inflammatory signals that can affect the liver, blood vessels, muscles, and insulin response.
So the number on the scale still matters – but it is only one part of a much bigger metabolic picture.
Visceral Fat Is Different From the Fat You Can Pinch
Not all body fat behaves in the same way.
Subcutaneous fat sits underneath the skin. It is the softer fat you can usually pinch around the abdomen, thighs, hips, or arms.
Visceral fat sits deeper inside the abdominal cavity, surrounding organs such as the liver and intestines.
Subcutaneous fat serves useful biological roles, including energy storage and insulation. In fact, healthy subcutaneous tissue can act as a relatively safe storage location for excess energy.
Problems may become more significant when that storage capacity is exceeded and more fat accumulates in visceral or ectopic locations such as the liver, muscle, pancreas, or around the heart.
A 2025 review highlighted fat distribution – not simply total fat mass – as an important contributor to insulin resistance, cardiovascular disease, diabetes, and fatty liver disease.
This is why asking only “How much do I weigh?” can miss an important question: “Where is that weight stored?”
BMI Cannot Measure Fat Distribution
BMI is calculated from height and weight. It is useful for estimating weight-related risk across populations, but it does not directly measure body fat.
A muscular athlete and a sedentary person could have the same BMI while having very different body compositions.
BMI also cannot distinguish visceral from subcutaneous fat.
This limitation matters because large studies and expert consensus statements show that waist circumference provides additional information about cardiometabolic risk beyond BMI.
That does not make BMI useless.
It means BMI works better as one screening measure among several, especially when combined with waist circumference, blood pressure, glucose, cholesterol, triglycerides, medical history, and other risk factors.
A normal scale weight does not automatically guarantee low metablic risk, just as a higher body weight does not reveal exactly where someone’s risk comes from.
Why Visceral Fat Is Linked to Insulin Resistance
One of the strongest metabolic associations with visceral fat is insulin resistance.
Insulin normally helps regulate blood glucose and suppresses the release of stored fatty acids from adipose tissue. When adipose tissue becomes insulin resistant, that control becomes less effective.
Visceral fat is particularly active in releasing free fatty acids and inflammatory signals. Some of these fatty acids drain toward the liver through the portal circulation, potentially contributing to altered liver metabolism.
Excess visceral fat is also associated with fat accumulation in skeletal muscle and liver, where lipid metabolites can interfere with normal insulin signalling.
Research has therefore moved away from viewing adipose tissue as simply passive energy storage. It is an endocrine and metabolic organ that communicates with many other tissues.
This helps explain why two people with similar body weight can have very different insulin sensitivity.
The Liver Is Closely Connected to Abdominal Fat
The relationship between visceral fat and liver health is especially important.
When adipose tissue releases excessive fatty acids into circulation, the liver may receive more fat than it can efficiently process. At the same time, insulin resistance can increase liver fat production and reduce normal metabolic regulation.
Over time, triglycerides can accumulate inside liver cells.
This process contributes to metabolic dysfunction-associated steatotic liver disease, or MASLD, the newer terminology used for fatty liver associated with metabolic dysfunction.
Research describes a strong two-way relationship between dysfunctional adipose tissue, insulin resistance, and fatty liver disease.
Liver fat also matters because it can worsen glucose regulation and abnormal lipid metabolism.
So someone may have relatively little visible body fat yet still carry metabolically important fat inside the abdomen or liver.
That is one reason appearance alone is a poor health assessment.
Visceral Fat Produces Inflammatory Signals
Adipose tissue is biologically active.
Fat cells and immune cells within adipose tissue can produce signalling molecules called adipokines and cytokines. When visceral tissue expands and becomes dysfunctional, the balance of those signals can shift.
Inflammatory signalling has been associated with impaired insulin action and vascular dysfunction.
Visceral obesity is also commonly associated with lower levels of adiponectin, a hormone linked with improved insulin sensitivity, while other inflammatory mediators may become elevated.
This does not mean visceral fat causes every case of inflammation.
Human metabolism is influenced by genetics, physical activity, diet, sleep, smoking, age, underlying diseases, and many other factors.
Still, chronic low-grade inflammation is one pathway researchers use to explain why excess visceral adiposity is associated with higher cardiometabolic risk.
Cardiovascular Risk Is Not Explained by Weight Alone
Heart disease risk provides another reason fat distribution matters.
An American Heart Association scientific statement notes that abdominal obesity measured by waist circumference is associated with cardiovascular risk independently of BMI.
Research using CT and MRI has also linked visceral and ectopic fat depots with poorer cardiovascular outcomes.
Visceral adiposity often travels with several other risk factors.
These can include elevated triglycerides, lower HDL cholesterol, higher blood pressure, insulin resistance, and abnormal glucose regulation.
Together, those changes can increase the likelihood of atherosclerosis and cardiovascular disease over time.
This is why focusing exclusively on losing kilograms can sometimes miss the real objective.
The larger goal is improving body composition and metabolic health, not simply making the scale number as low as possible.
Waist Circumference Is a Useful – But Imperfect – Clue
The most accurate measurements of visceral fat generally come from imaging methods such as CT or MRI.
Those tools are useful in research and specific clinical situations but are too expensive and impractical for routine monitoring.
Waist circumference offers a simpler alternative.
It cannot directly distinguish visceral fat from abdominal subcutaneous fat, but it provides useful information about central adiposity and adds risk information beyond BMI.
International experts have argued that waist circumference deserves much greater use in routine assessment.
The exact risk thresholds can vary by sex, ethnicity, and clinical guideline, so one global cutoff is not appropriate for everyone.
The trend over time can also be informative.
A shrinking waist while body weight changes only modestly may still indicate a meaningful improvement in abdominal adiposity.
That is another reason scale weight should not be evaluated seperately from other measures.
Can You Have Too Much Visceral Fat at a “Normal” Weight?
Yes.
Some people have a BMI within the conventional healthy range but carry relatively little muscle and more abdominal or ectopic fat.
Others may have fatty liver, high triglycerides, impaired glucose regulation, or elevated blood pressure without appearing visibly overweight.
NIDDK notes that excess abdominal fat can increase health risk even in people who are not classified as overweight.
This does not mean every naturally slim person needs abdominal imaging.
It means body size should never replace actual health assessment.
Blood pressure, blood lipids, glucose markers, activity level, family history, sleep, smoking status, and waist size can provide valuable context.
A person’s appearance is not a reliable shortcut for deciding whether their metabolism is healthy.
Exercise Can Reduce Visceral Fat Even Without Dramatic Weight Loss
One encouraging feature of visceral fat is that it can respond to lifestyle change.
Regular aerobic exercise can reduce abdominal and visceral fat, sometimes even when total body weight changes relatively little.
Resistance training also matters because maintaining or increasing skeletal muscle supports glucose disposal, physical function, and healthier body composition.
Expert consensus on waist circumference notes that exercise and dietary interventions can reduce abdominal size, and those improvements may occur even without a major change in BMI.
This helps explain why exercise progress should not always be judged by the scale.
Someone may lose visceral fat, gain or preserve muscle, improve insulin sensitivity, and reduce waist circumference while their body weight barely moves.
From a health perspective, that could still be a meaningful improvement.
The body is changing even if the bathroom scale is not especially impressed.
Diet, Sleep, and Daily Habits Still Matter
No single food specifically “burns” visceral fat.
Changes usually come from a broader shift in energy balance and metabolic health.
Eating patterns based largely on vegetables, fruit, legumes, whole grains, adequate protein, healthy fats, and minimally processed foods can support weight management and cardiometabolic health when they fit overall energy needs.
Sleep and physical activity matter as well.
Chronic sleep disruption can influence appetite, glucose metabolism, and energy regulation, while long periods of sedentary behaviour can work against metabolic health even when someone occasionally exercises.
Alcohol can also contribute significant energy and may promote liver fat in susceptible individuals.
The most useful strategy is usually the one a person can follow consistantly, not an extreme plan that produces rapid weight loss and is abandoned a few weeks later.
Weight Loss Can Help, but the Quality of the Change Matters
For people carrying excess body fat, losing weight often improves blood pressure, glucose regulation, triglycerides, and other metabolic markers.
But the benefits are not simply caused by making the total body mass smaller.
Reductions in visceral fat and liver fat can contribute significantly to metabolic improvement.
This explains why treatments that produce sustained fat loss may improve several obesity-related diseases at once.
At the same time, people should avoid assuming that thinner always means healthier.
Excessive calorie restriction can also reduce muscle and bone mass if nutrition and physical activity are poorly managed.
A better target is improved body composition and lower cardiometabolic risk.
The scale is useful – but it should work alongside waist measurements, laboratory results, fitness, and other indicators rather than replacing them.
Visceral fat matters more than body weight alone because fat location strongly influences metabolic risk.
Fat stored deep inside the abdomen is linked with insulin resistance, abnormal lipid metabolism, fatty liver disease, inflammation, and cardiovascular risk.
BMI and body weight can identify broad trends, but they cannot reveal where fat is stored or distinguish fat from muscle.
That is why waist circumference, blood pressure, glucose, lipid levels, lifestyle, and medical history provide important extra context.
Instead of chasing one ideal scale number, focus on the bigger picture: regular movement, resistance training, sustainable nutrition, adequate sleep, and improving metabolic markers over time.
If you are concerned about abdominal fat or cardiometabolic risk, discuss appropriate screening with a qualified healthcare professional.